
Skin Science · Clinical Distinctions
Neuromodulators vs. fillers: a clinically important distinction
These two treatment categories are frequently conflated. They operate on fundamentally different anatomical targets, produce different outcomes, and carry fundamentally different risk profiles.
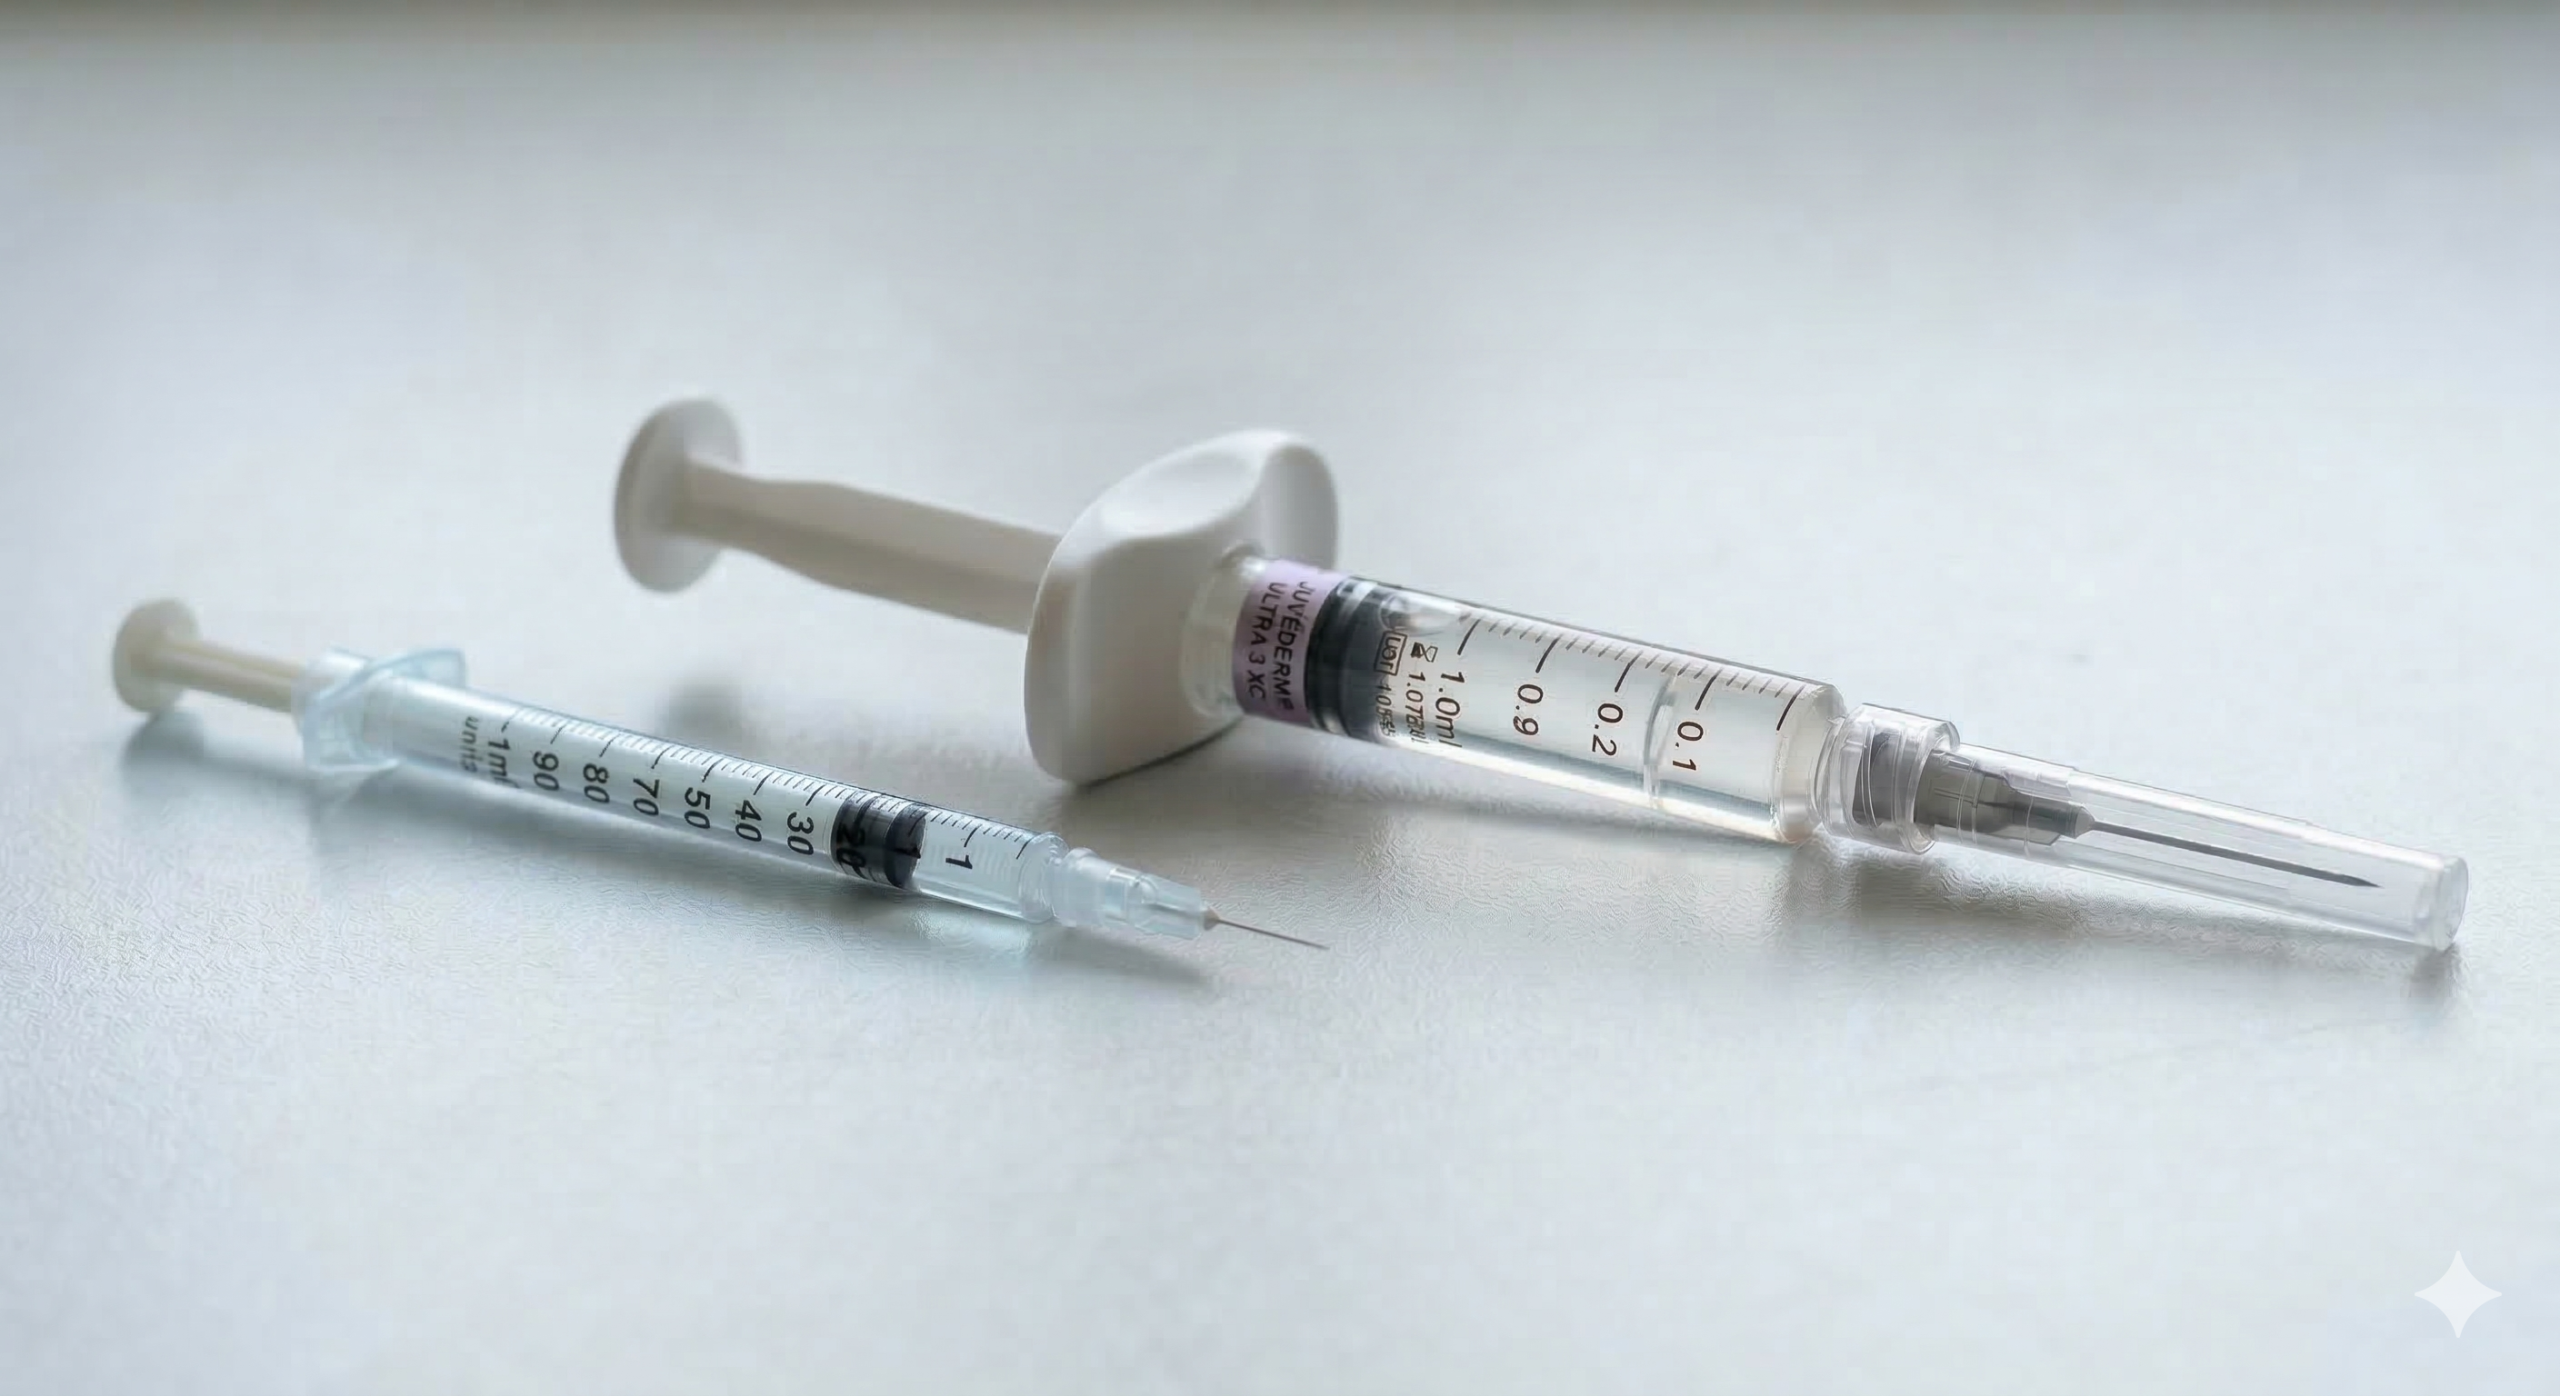
What neuromodulators do
Neuromodulators, including botulinum toxin products such as Botox and Dysport, act on the neuromuscular junction. They temporarily inhibit the release of acetylcholine, the neurotransmitter responsible for signaling muscle contraction. The targeted muscle relaxes, softening the overlying skin crease.
The effect is specific to the injected muscle, reversible as the protein metabolizes, and does not alter tissue structure beneath the skin. The safety profile of botulinum toxin has been extensively documented across aesthetic and medical applications over more than three decades. Adverse events, when they occur, are mild and fully reversible.
What fillers do
Dermal fillers add volume beneath the skin surface to restore or reshape facial contours. Most contemporary fillers use cross-linked hyaluronic acid (HA), a naturally occurring polysaccharide, as the volumizing agent. HA fillers are reversible with hyaluronidase enzyme injection. Other filler materials (calcium hydroxylapatite, poly-L-lactic acid, permanent fillers) are not reversible or only partially so.
Fillers address a different problem than neuromodulators (a practical example is the lip flip versus lip filler): volume loss and structural hollowing, rather than muscle-driven lines. The clinical indications are distinct, and the two are not substitutes for each other.
Risk profiles compared
The risk profile of neuromodulators is well-characterized and limited primarily to localized effects: temporary asymmetry if product migrates slightly, mild bruising at injection sites, and in rare cases transient ptosis (drooping) of a brow or eyelid that resolves as the protein metabolizes. These are temporary and require no intervention.
Fillers carry a distinct and broader set of risks. Vascular occlusion, where filler material enters or compresses a blood vessel, is rare but potentially serious, and can result in tissue necrosis or, in extreme cases, vision impairment. Chronic foreign body inflammatory response produces low-grade tissue reactions in some patients. Product migration is documented particularly with repeated treatment over time. Tyndall effect (a bluish discolouration visible through the skin from superficially placed HA) requires dissolving. These risks require different clinical skills and emergency protocols to manage.
THE CUMULATIVE TISSUE CHANGE CONCERN
Repeated hyaluronic acid filler over several years can alter the mechanical properties of the tissue into which it is injected. The hydrophilic nature of HA attracts water, which can distort the area over time in ways that become difficult to reverse, separate from the acute risks of each individual treatment.
Why HALO does not offer filler treatments
HALO’s treatment philosophy prioritizes interventions with strong evidence bases, clear risk profiles, and outcomes that support long-term skin health. We address skin quality, muscle activity, and cellular regeneration, mechanisms with direct relevance to skin longevity.
Filler-driven volume restoration does not address any underlying mechanisms of skin aging. Its risk profile is distinct from the treatments we offer and requires different emergency preparedness and clinical management protocols. For patients seeking improvement in skin quality, hydration, texture, and the appearance of lines, the combination of Botox, polynucleotides, PRP, and infusions addresses these concerns through evidence-based regenerative mechanisms, without the risks associated with exogenous volumizing agents.
References
- Dressler D, Adib Saberi F. Botulinum toxin: mechanisms of action. Eur Neurol. 2005;53(1):3-9. PMID 15650306.
- Brin MF, Maltman J, Chapman MA, et al. Versatility of OnabotulinumtoxinA in Aesthetic Medicine. Dermatol Surg. 2024;50(9S):S12-S17. PMID 39196828.
- Jia Z, Lu H, Yang X, et al. Adverse Events of Botulinum Toxin Type A in Facial Rejuvenation: A Systematic Review and Meta-Analysis. Aesthetic Plast Surg. 2016;40(5):769-777. PMID 27495260.
- Liu J, Gao M, Hu H, et al. Facial Injectable Fillers in Aesthetic Medicine: Clinical Applications and Safety Strategies. Med Sci Monit. 2025;31:e949944. PMID 41199535.
- Kroumpouzos G, Treacy P. Hyaluronidase for Dermal Filler Complications: Review of Applications and Dosage Recommendations. JMIR Dermatol. 2024;7:e50403. PMID 38231537.
- Beleznay K, Carruthers JD, Humphrey S, et al. Avoiding and Treating Blindness From Fillers: A Review of the World Literature. Dermatol Surg. 2015;41(10):1097-1117. PMID 26356847.
- Artzi O, Cohen JL, Dover JS, et al. Delayed Inflammatory Reactions to Hyaluronic Acid Fillers: A Literature Review and Proposed Treatment Algorithm. Clin Cosmet Investig Dermatol. 2020;13:371-378. PMID 32547150.
- Trinh LN, McGuigan KC, Gupta A. Delayed Complications following Dermal Filler for Tear Trough Augmentation: A Systematic Review. Facial Plast Surg. 2022;38(3):250-259. PMID 34666405.
- Master M, Azizeddin A, Master V. Hyaluronic Acid Filler Longevity in the Mid-face: A Review of 33 Magnetic Resonance Imaging Studies. Plast Reconstr Surg Glob Open. 2024;12(7):e5934. PMID 39015357.
Ready to put this into practice?
Consultations at HALO are free and never obligatory. Bring your questions.
Book Now